
Intermediate-1 Myelofibrosis Patient Profile | Jakafi®/Jakafi XR™ (ruxolitinib) Skip to main content
Jane experiencing myelofibrosis symptoms at home Jane_Profile-mobile.

This profile represents a hypothetical patient.

Can Jane afford to wait with her increasing spleen volume?

Evaluating JANE

56-year-old1 executive assistant

  • Recently diagnosed with primary MF after incidental findings in routine blood work

Symptoms:

Mild fatigue, some abdominal discomfort, and occasional night sweats. Jane reports her symptoms are tolerable, but she feels something is wrong. MPN-SAF TSS: 15 (low)1,2

Physical exam:

Spleen palpable 5 cm below LCM1

DIPSS score:

Intermediate-1 (due to her constitutional symptoms)3

Is Jane really feeling OK?

She has considerable symptoms and her spleen volume is increasing, which may impact overall survival3,4

Spleen volume and risk of death

Increasing spleen volume is associated with a 14% increase in mortality risk4
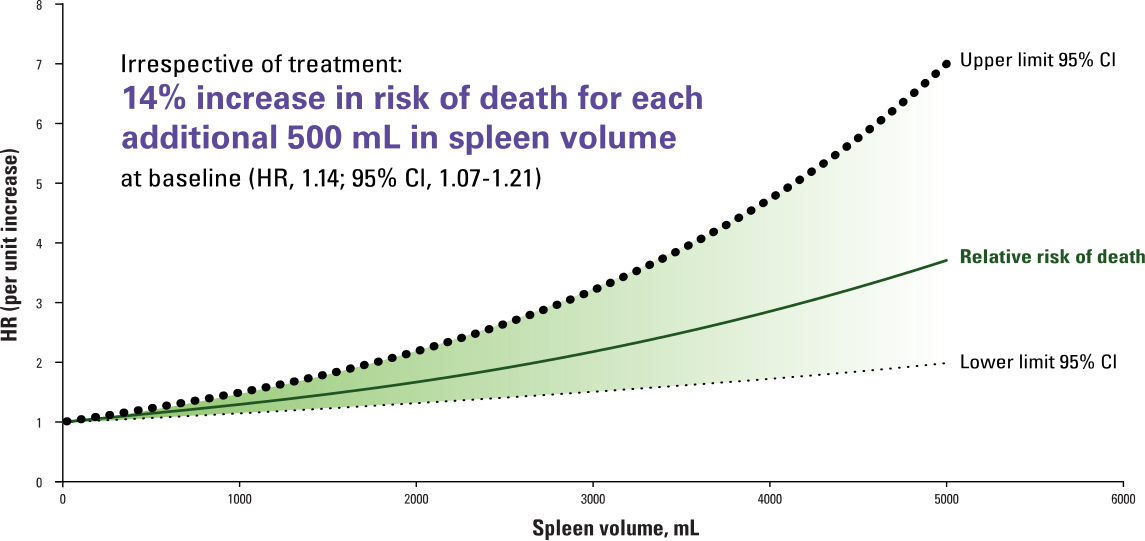
Relationship between spleen volume and risk of death

Post Hoc Pooled Analysis of Overall Survival in the COMFORT Studies (N=528) Over 3 Years4*

Line graph showing death risk increasing with spleen volume

In a study of 1054 patients with primary MF†

9 out of 10 had a palpable spleen at diagnosis5

  • A palpable spleen of ≥5 cm below the LCM constitutes progressive disease,‡ according to the IWG-MRT and ELN response criteria6
  • *A post hoc pooled analysis of OS with ruxolitinib was performed using data from 2 phase 3 studies (N=528): COMFORT-I, a randomized, double-blind, placebo-controlled study with 309 patients with intermediate-2–risk or high-risk MF, and COMFORT-II, a randomized, open-label study with 219 patients with intermediate-2–risk or high-risk MF. The primary endpoint in both studies was the proportion of patients achieving a ≥35% reduction in spleen volume (measured by CT or MRI)—at week 24 in COMFORT-I and at week 48 in COMFORT-II.1,4,7
  • †Data were available for 768 patients, 681 of whom had palpable splenomegaly.5
  • ‡Progressive disease assignment for splenomegaly requires confirmation by CT or MRI showing a ≥25% increase in spleen volume from baseline. Baseline values for both physical examination and imaging studies refer to pretreatment baseline and not to posttreatment measurements.6

CI=confidence interval; COMFORT=COntrolled MyeloFibrosis study with ORal JAK inhibitor Treatment; CT=computed tomography; DIPSS=Dynamic International Prognostic Scoring System; ELN=European LeukemiaNet; HR=hazard ratio; IWG-MRT=International Working Group-Myeloproliferative Neoplasms Research and Treatment; JAK=Janus kinase; LCM=left costal margin; MF=myelofibrosis; MPN-SAF=Myeloproliferative Neoplasm Symptom Assessment Form; MRI=magnetic resonance imaging; OS=overall survival; SVR=spleen volume reduction; TSS=Total Symptom Score.

References: 1. Verstovsek S, Mesa RA, Gotlib J, et al. A double-blind, placebo-controlled trial of ruxolitinib for myelofibrosis. N Engl J Med. 2012;366(9):799-807. Supplemental appendix available at: https://www.nejm.org/doi/full/10.1056/nejmoa1110557. 2. Emanuel RM, Dueck AC, Geyer HL, et al. Myeloproliferative neoplasm (MPN) symptom assessment form total symptom score: prospective international assessment of an abbreviated symptom burden scoring system among patients with MPNs. J Clin Oncol. 2012;30(33):4098-4103. 3. Passamonti F, Cervantes F, Vannucchi AM, et al. A dynamic prognostic model to predict survival in primary myelofibrosis: a study by the IWG-MRT (International Working Group for Myeloproliferative Neoplasms Research and Treatment). Blood. 2010;115(9):1703-1708. 4. Vannucchi AM, Kantarjian HM, Kiladjian J-J, et al; on behalf of the COMFORT Investigators. A pooled analysis of overall survival in COMFORT-I and COMFORT-II, 2 randomized phase III trials of ruxolitinib for the treatment of myelofibrosis. Haematologica. 2015;100(9):1139-1145. Supplemental information available at: https://doi.org/10.3324/haematol.2014.119545. 5. Cervantes F, Dupriez B, Pereira A, et al. New prognostic scoring system for primary myelofibrosis based on a study of the International Working Group for Myelofibrosis Research and Treatment. Blood. 2009;113(13):2895-2901. 6. Tefferi A, Cervantes F, Mesa R, et al. Revised response criteria for myelofibrosis: International Working Group-Myeloproliferative Neoplasms Research and Treatment (IWG-MRT) and European LeukemiaNet (ELN) consensus report. Blood. 2013;122(8):1395-1398. 7. Harrison CN, Vannucchi AM, Kiladjian J-J, et al; on behalf of the COMFORT-II investigators. Long-term findings from COMFORT-II, a phase 3 study of ruxolitinib vs best available therapy for myelofibrosis. Leukemia. 2016;30(8):1701-1707.


IMPORTANT SAFETY INFORMATION

Warnings and Precautions

Thrombocytopenia, Anemia and Neutropenia

  • JAKAFI®/JAKAFI XR™ (ruxolitinib) can cause dose‑related effects of thrombocytopenia, anemia and neutropenia. Perform a pre‑treatment complete blood count (CBC) and monitor CBCs every 2 to 4 weeks until doses are stabilized, and then as clinically indicated.
  • Manage thrombocytopenia by reducing the dose or temporarily interrupting JAKAFI/JAKAFI XR. Platelet transfusions may be necessary.
  • Patients developing anemia may require blood transfusions and/or dose modifications of JAKAFI/JAKAFI XR.
  • Severe neutropenia (ANC <0.5 × 10⁹/L) was generally reversible by withholding JAKAFI/JAKAFI XR until recovery.

INDICATIONS AND USAGE

JAKAFI®/JAKAFI XR™ (ruxolitinib) is for treatment of intermediate or high‑risk myelofibrosis (MF), including primary MF, post–polycythemia vera MF and post–essential thrombocythemia MF in adults.

JAKAFI/JAKAFI XR is for treatment of polycythemia vera (PV) in adults who have had an inadequate response to or are intolerant of hydroxyurea.

JAKAFI/JAKAFI XR is for treatment of steroid‑refractory acute graft‑versus‑host disease (aGVHD) in adult and pediatric patients 12 years and older.

JAKAFI/JAKAFI XR is for treatment of chronic graft‑versus‑host disease (cGVHD) after failure of one or two lines of systemic therapy in adult and pediatric patients 12 years and older.

Risk of Infection

  • Serious bacterial, mycobacterial, fungal and viral infections have occurred. Delay starting JAKAFI/JAKAFI XR until active serious infections have resolved. Observe patients receiving JAKAFI/JAKAFI XR for signs and symptoms of infection and manage promptly.

Tuberculosis

  • Tuberculosis (TB) infection with JAKAFI/JAKAFI XR has been reported. Observe patients taking JAKAFI/JAKAFI XR for signs and symptoms of active TB and manage promptly. Prior to initiating, evaluate patients for TB risk factors and test those at higher risk for latent infection. Consult a physician with expertise in the treatment of TB before starting in patients with evidence of active or latent TB. Continuation during treatment of active TB should be based on the overall risk‑benefit determination.

Progressive Multifocal Leukoencephalopathy

  • Progressive multifocal leukoencephalopathy (PML) has occurred with JAKAFI/JAKAFI XR treatment. If PML is suspected, stop JAKAFI/JAKAFI XR and evaluate.

Herpes Zoster and Herpes Simplex

  • Herpes zoster infection, reactivation and/or dissemination has been reported in patients receiving JAKAFI/JAKAFI XR. Advise patients about early signs and symptoms of herpes zoster and seek treatment. Monitor patients for the development of herpes simplex infections. If a patient develops evidence of dissemination of herpes simplex, consider interrupting treatment.

Hepatitis B

  • Increases in hepatitis B viral load with or without associated elevations in alanine aminotransferase and aspartate aminotransferase have been reported in patients with chronic hepatitis B virus (HBV) infections.

Symptom Exacerbation Following Interruption or Discontinuation of Treatment

  • When discontinuing JAK‑Inhibitors, including JAKAFI/JAKAFI XR, myeloproliferative neoplasm‑related signs and symptoms may flare. After discontinuation, some patients with myelofibrosis have experienced fever, respiratory distress, hypotension, disseminated intravascular coagulation (DIC), or multi‑organ failure. If any of these occur after discontinuation or while tapering JAKAFI/JAKAFI XR, evaluate and treat any intercurrent illness and consider restarting or increasing the dose. Instruct patients not to interrupt or discontinue JAKAFI/JAKAFI XR without consulting their physician. When discontinuing or interrupting JAKAFI/JAKAFI XR for reasons other than life‑threatening toxicities, consider gradual tapering rather than abrupt discontinuation.

Non‑Melanoma Skin Cancer (NMSC)

  • NMSC including basal cell, squamous cell, and Merkel cell carcinoma have occurred. Perform periodic skin examinations.

Lipid Elevations

  • Treatment with JAKAFI/JAKAFI XR has been associated with increases in total cholesterol, low‑density lipoprotein cholesterol, and triglycerides. Assess lipid parameters 8‑12 weeks after initiation.

Major Adverse Cardiovascular Events (MACE)

  • Another JAK‑inhibitor has increased the risk of major adverse cardiovascular events (MACE), including cardiovascular death, myocardial infarction, and stroke (compared to those treated with TNF blockers), in patients with rheumatoid arthritis, a condition for which JAKAFI/JAKAFI XR is not indicated. Consider the benefits and risks for the individual patient prior to initiating or continuing therapy, particularly in patients who are current or past smokers and patients with other cardiovascular risk factors. Patients should be informed about the symptoms of serious cardiovascular events and the steps to take if they occur.

Thrombosis

  • Another JAK‑inhibitor has increased the risk of thrombosis, including deep venous thrombosis (DVT), pulmonary embolism (PE), and arterial thrombosis (compared to those treated with TNF blockers), in patients with rheumatoid arthritis, a condition for which JAKAFI/JAKAFI XR is not indicated. In patients with myelofibrosis (MF) and polycythemia vera (PV), the rates of thromboembolic events were similar in JAKAFI/JAKAFI XR and control treated patients. Patients with symptoms of thrombosis should be promptly evaluated and treated appropriately.

Secondary Malignancies

  • Another JAK‑inhibitor has increased the risk of lymphoma and other malignancies, excluding NMSC (compared to those treated with TNF blockers), in patients with rheumatoid arthritis, a condition for which JAKAFI/JAKAFI XR is not indicated. Patients who are current or past smokers are at additional increased risk.

Adverse Reactions

  • In myelofibrosis, the most common hematologic adverse reactions (incidence >20%) were thrombocytopenia and anemia. The most common nonhematologic adverse reactions (incidence ≥15%) were bruising, dizziness and headache.
  • In polycythemia vera, the most common hematologic adverse reactions (incidence >20%) were anemia and thrombocytopenia. The most common nonhematologic adverse reactions (incidence ≥15%) were diarrhea and dizziness.
  • In acute graft‑versus‑host disease, the most common hematologic adverse reactions (incidence >50%) were anemia, thrombocytopenia and neutropenia. The most common nonhematologic adverse reactions (incidence >50%) were infections (pathogen not specified) and edema.
  • In chronic graft‑versus‑host disease, the most common hematologic adverse reactions (incidence >35%) were anemia and thrombocytopenia. The most common nonhematologic adverse reactions (incidence ≥20%) were infections (pathogen not specified) and viral infections.

Drug Interactions

  • Avoid concomitant use with fluconazole doses greater than 200 mg. Dose modifications may be required when administering fluconazole doses of 200 mg or less, or with strong CYP3A4 inhibitors, or in patients with renal or hepatic impairment. Patients should be closely monitored and the dose titrated based on safety and efficacy.

Pregnancy

  • Use during pregnancy is not recommended and should only be used if the potential benefit justifies the potential risk to the fetus. Women taking JAKAFI/JAKAFI XR should not breastfeed during treatment and for 2 weeks after the final dose.

Please see Full Prescribing Information for JAKAFI/JAKAFI XR.


